

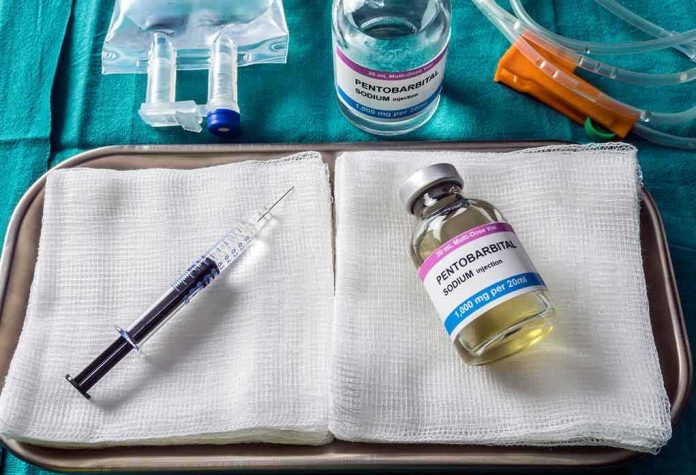
The hard problem in modern lethal injection is not pharmacology but plumbing: when the intravenous route fails or is uncertain, everything that follows—drug effect, humaneness, legality—rests on guesswork rather than physiology.
At a Glance
- Accounts from Christa Pike’s execution attempt describe repeated IV failures, staff concern that a vein “might be blowing,” and resistance to a saline push before drugs were delivered.
- Tennessee officials have asserted protocol compliance and the historical effectiveness of their lethal-injection drug but have not provided a granular technical account disputing IV-access problems.
- Venous-access breakdowns are the most common point of failure in lethal injections nationwide; Pike’s case tracks that pattern rather than defying it.
- The evidentiary gap—limited independent documentation from the execution team—keeps key questions unresolved and invites a methodical reconstruction to determine what actually happened.
What the Pike case shows about the real failure mode of lethal injection
According to a sworn declaration by defense attorney Randy Spivey and contemporaneous filings, the team attempting to execute Christa Pike cycled through roughly ten needles across multiple sites before settling on a line; one team member voiced that a vein “might be blowing,” and staff reportedly encountered resistance pushing saline through the final IV just before proceeding with the lethal dose. In plain clinical terms, those cues—multiple sticks, talk of a “blown” vein, and a difficult flush—are classic red flags for malposition, infiltration, or venous spasm. If the catheter was not intravascular, the drug could have pooled in soft tissue rather than entering systemic circulation at the intended rate or at all. That is not a philosophical problem; it is a mechanical one with predictable pharmacologic consequences.
The state’s public posture has been narrow. Tennessee’s Department of Correction has said it followed every step of its authorized protocol, that its chosen chemical has been consistently effective, and that the protocol did not allow additional procedures beyond those performed that evening. That statement affirms process but does not rebut the specific access-failure scenario. And the best national data we have suggest such scenarios are not anomalies. Surveys and historical analyses place botched lethal-injection attempts at several percent of cases, with IV-access failure the single most common reason for abandonment of an execution mid-procedure.
Mechanism: why a “blown” IV defeats an otherwise potent drug
Lethal injection protocols hinge on reliable venous access. Pentobarbital, the barbiturate many states rely on, must reach the bloodstream quickly and in full dose to produce deep coma followed by respiratory and cardiac arrest. A functioning line demonstrates three basic traits: free blood return (or clear intravascular placement by visualization), a smooth saline flush with minimal resistance, and stable catheter position secured against dislodgment. When a vein “blows”—a colloquialism for rupture or loss of intraluminal access—infusate extravasates into surrounding tissue. Barbiturate deposited subcutaneously absorbs slowly and unpredictably; a portion may never reach effective circulatory concentrations. The result is clinical limbo: insufficient anesthesia and delayed toxicity, a worst-of-both-worlds outcome for any procedure premised on swift, certain onset.
Every cue reported from Pike’s attempt maps to this failure chain: repeated cannulation attempts (suggesting difficult veins), contemporaneous staff doubt about patency, and resistance to a saline push prior to drug administration. None conclusively proves extravasation on its own; together, they describe the canonical setup for it. In any medical context outside an execution chamber, those signs would trigger immediate troubleshooting—new site, ultrasound guidance, or escalation to central access—before delivering high-stakes medication.
History and pattern: Pike’s case is an instance of a known systemic vulnerability
Lethal injection’s public-facing controversy often centers on the drugs. The operational reality is less dramatic: most breakdowns begin at the skin. Over four decades, the largest share of botched executions has involved IV problems, including cases abandoned after prolonged, unsuccessful cannulation attempts. General reference syntheses and case surveys document the recurring triad: difficult venous access, non-expert operators working under secrecy constraints, and limited physiological monitoring that would otherwise expose line failure in real time. Against that backdrop, the Pike accounts do not read as outliers; they track the base rate.
Tennessee’s recent experience reinforces the point. Separate reporting has noted prior difficulties establishing access in another execution attempt, and litigation over Pike’s medical history previewed access risk—even if a special master did not find a pre-execution showing of substantial risk of severe pain. That ex ante ruling does not resolve what happened in the chamber; it simply shows how easy it is to discount a hazard until it materializes in practice.
Where the evidence is strong—and where it is thin
What is strongest are the internally consistent, time-stamped operational details in the defense declaration: the number of sticks, the contemporaneous “might be blowing” exchange, and the resistant saline flush. Those are the right details to matter mechanistically, and they align with what experienced clinicians would flag as line failure. What is thin are the official, independent artifacts that could settle the matter definitively: a complete attempt-by-attempt IV log, real-time monitoring records, drug-volume reconciliation, photos of insertion sites, and toxicology showing how much pentobarbital reached circulation. Absent that record, causation cannot be proven to the gram, but the pattern of cues places the burden of technical explanation squarely on the state that controlled the environment.
The state’s counter is procedural rather than forensic: protocol compliance and a drug with a track record of effectiveness. Those assurances are not trivial—standardization reduces risk—but they are not a rebuttal to a concrete access failure. Potent drugs do not work if they are not delivered into a vein, and a protocol that lacks escalation paths when patency is uncertain bakes fragility into the system.
🚨 BREAKING UPDATE: CHRISTA PIKE SURVIVES EXECUTION — NOW NEW QUESTIONS ARE EMERGING! 🚨
🇺🇸 TENNESSEE — In an extraordinary development, death row inmate Christa Gail Pike is alive after receiving two doses of lethal injection drugs during a failed execution attempt on September… pic.twitter.com/0dtsKQ2TED
— Starsstripes&coffee (@Starsstripesc) October 18, 2026
What a competent reconstruction would require
Because this failure mode is technical and verifiable, the path forward is likewise technical. A meaningful reconstruction would gather, at minimum: sworn statements from each IV team member describing site choices, number of attempts, visual cues, and the feel of the saline push; the full execution log, including timing and volumes of each flush and drug; any video or audio from the chamber; post-event clinical records documenting insertion sites, swelling, or tissue injury; and toxicology or blood-gas data indicating barbiturate levels after the attempt. With that file, an anesthesiology and vascular-access panel could model drug kinetics under plausible extravasation scenarios and conclude, within credible intervals, how much drug likely reached circulation and on what timeline. That is how hospitals audit adverse events after difficult IV starts; the same rigor is available here if the records are produced.
Implications: designing protocols for the failure we actually see
If policymakers take the Pike pattern seriously, three design choices follow. First, treat IV access as the critical path: mandate ultrasound-guided peripheral placement by credentialed specialists and document a successful, low-resistance saline flush with an objective measure before induction. Second, require a clear escalation ladder—second site, larger-bore catheter, or central access by a qualified physician—when patency is uncertain. Third, recordkeeping and monitoring must be robust enough to detect and prove patency in real time: continuous visual verification of the site, pressure-sensing infusion pumps, and transparent logs subject to independent audit. These are unremarkable safety practices in clinical medicine; lethal-injection protocols regularly omit or blunt them under the combined pressures of secrecy, logistics, and professional ethics constraints that limit clinician involvement.
Bottom line
Pike’s failed execution is best understood not as an inscrutable anomaly but as a textbook instance of lethal injection’s dominant operational risk: uncertain intravenous access. The specific cues reported—multiple sticks, staff voicing a “blown” vein, and a resistant saline flush—fit the mechanism by which even a reliable drug fails. Tennessee’s assurance of protocol compliance does not answer that technical failure; only a full, auditable reconstruction can. Until protocols are engineered for the failure we actually see, not the idealized procedure on paper, the system will continue to confuse drug efficacy with delivery certainty—and repeatably get the most important variable wrong.
Sources:
washingtontimes.com, apnews.com, cbc.ca, union-bulletin.com, jacksonville.com, reuters.com, guelph.ctvnews.ca, npr.org, pbs.org



